
Loading...
Loading...
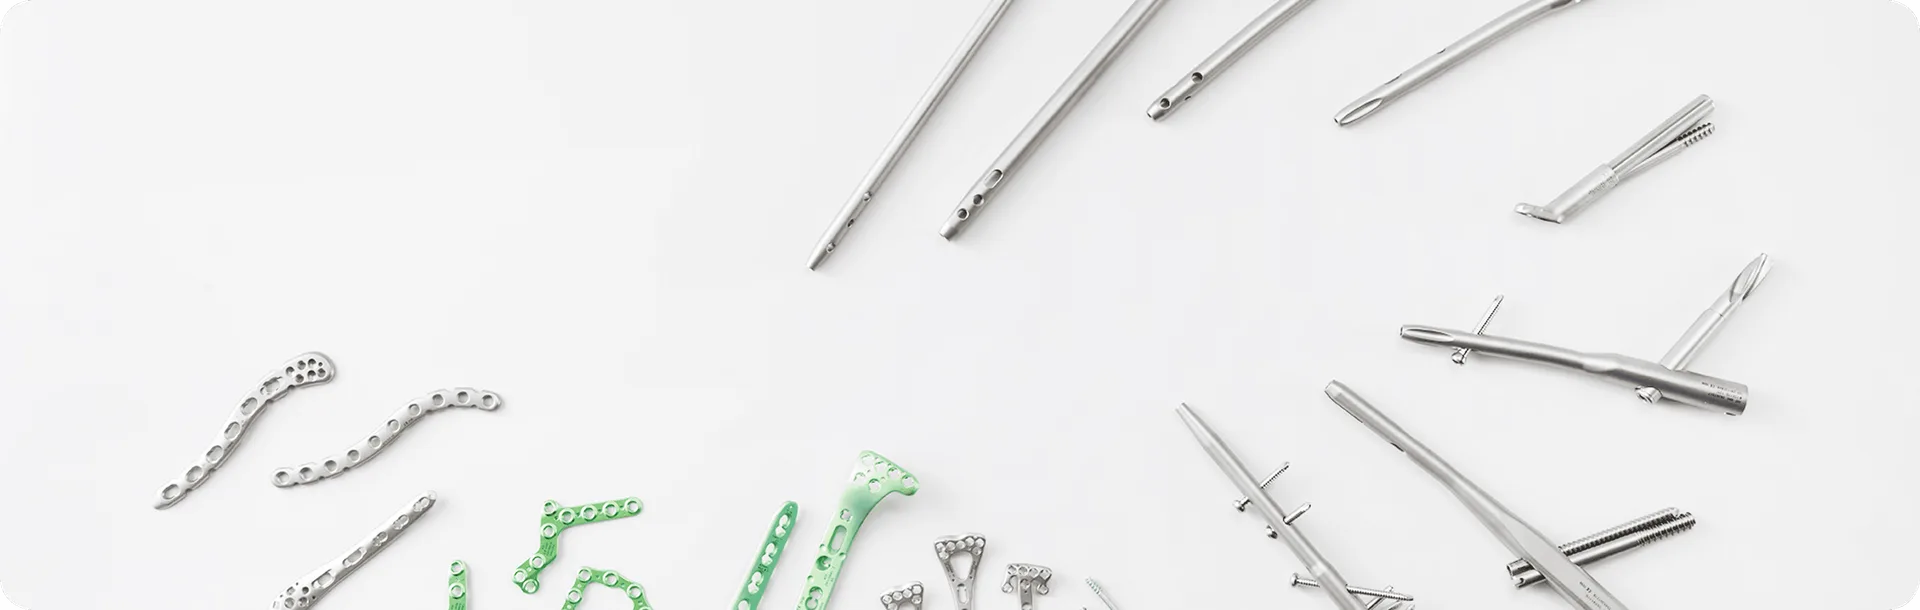

Designed for proximal humeral and humeral shaft fractures, featuring multi-planar locking technology to deliver angular and rotational stability.

PFNA (Proximal Femoral Nail Antirotation) is indicated for unstable intertrochanteric and subtrochanteric fractures, with helical blade structure for enhanced antirotation performance.

Integrated Intertrochanteric Nail adopts dual-screw structure for antirotation, compression and biomechanical stability, indicated for intertrochanteric and subtrochanteric femoral fractures.
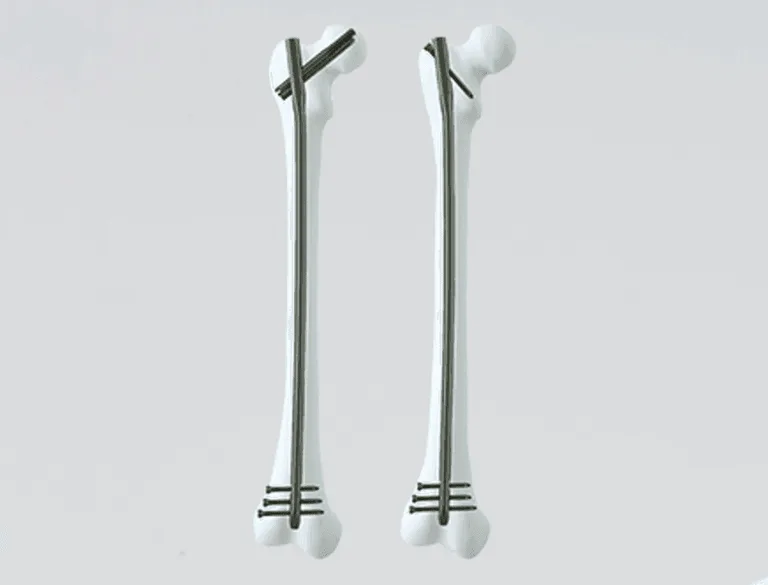
Antegrade femoral locking nail is designed for complex femoral fractures (proximal to shaft), with integrated locking system providing rotational stability, controlled compression and strong load-sharing capacity.
Tibial locking nail is indicated for stable and unstable tibial fractures (proximal to distal), featuring anatomical geometry and multi-planar locking technology for superior biomechanical stability.
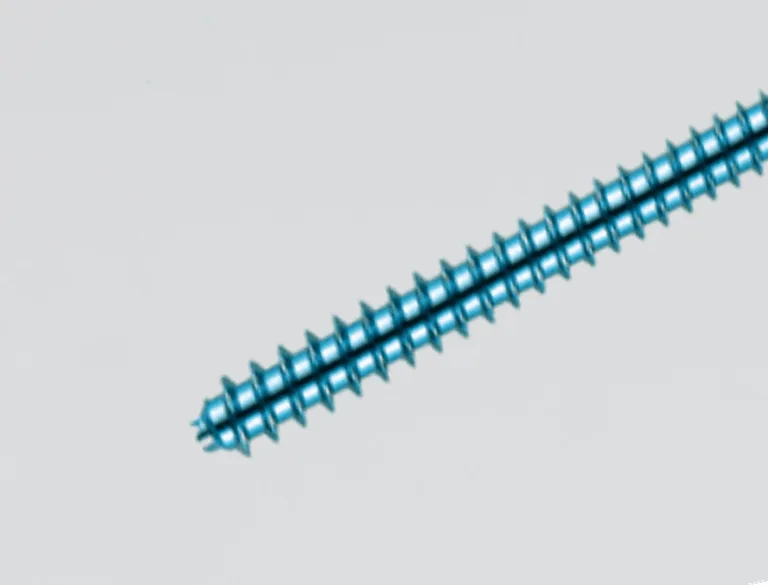
Headless compression cannulated screw is designed for small bone fractures and osteotomies requiring low-profile fixation, with fully buried headless design to deliver controlled compression while minimizing soft tissue irritation.

Countersinkable compression cannulated screw is indicated for small bone fractures around joints and thin soft tissue areas, with countersunk head to reduce soft tissue irritation and hardware prominence.

Compression cannulated screw is indicated for stable internal fixation of small bone fractures and osteotomies, providing controlled interfragmentary compression with cannulated design for guide-wire assisted minimally invasive insertion.
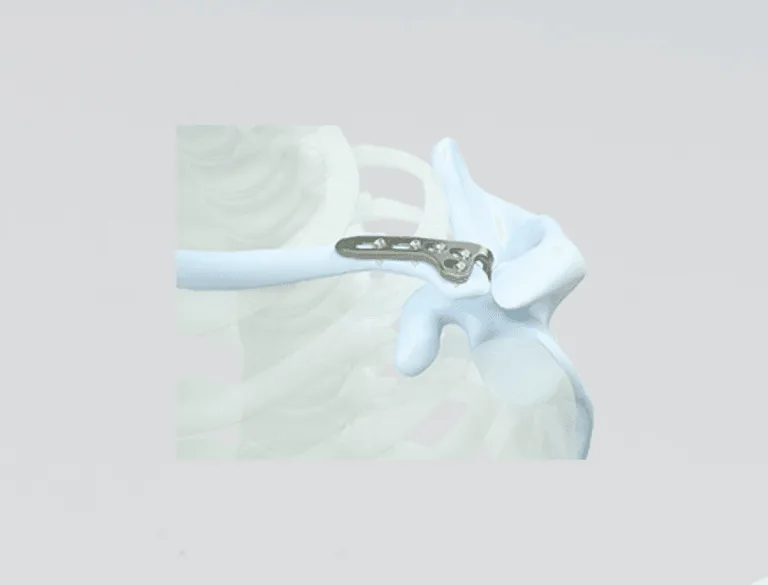
Clavicle hook locking compression plate is indicated for distal clavicle fractures and acromioclavicular joint dislocations, combining locking plate fixation with clavicular hook extension to provide lever stability and maintain reduction via subacromial hook support.

Proximal humeral locking plate is indicated for proximal humerus fractures, with region-specific anatomical contouring to provide stable fixation for humeral head, tuberosities and metaphysis.

Medial distal humeral locking plate is indicated for complex distal humerus fractures, with anatomical contour design to provide angular stable fixation while preserving soft tissue integrity.
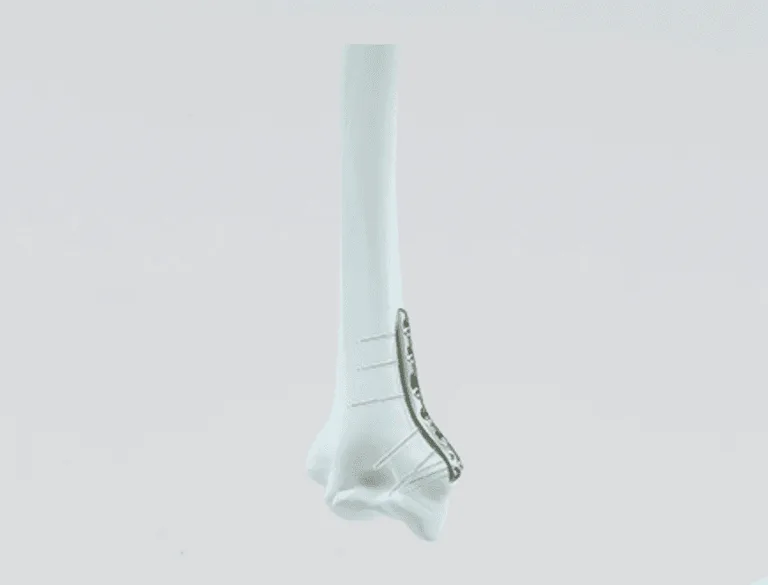
Lateral distal humeral locking plate is indicated for complex distal humerus fractures involving lateral column and posterior (dorsal) side, with pre-contoured anatomical design for angular stable fixation.

Lateral distal humeral locking plate is indicated for complex distal humerus fractures involving lateral column and posterior (dorsal) side, with pre-contoured anatomical design for angular stable fixation.

Posterolateral distal humeral locking plate is designed for complex distal humerus fractures involving lateral column, combining dorsolateral plating principle with extended lateral support to enhance fixation strength for comminuted and osteoporotic fractures.

Olecranon locking plate is indicated for olecranon and proximal ulna fractures, with anatomical contour design to provide stable angular fixation for intra-articular and extra-articular fractures.
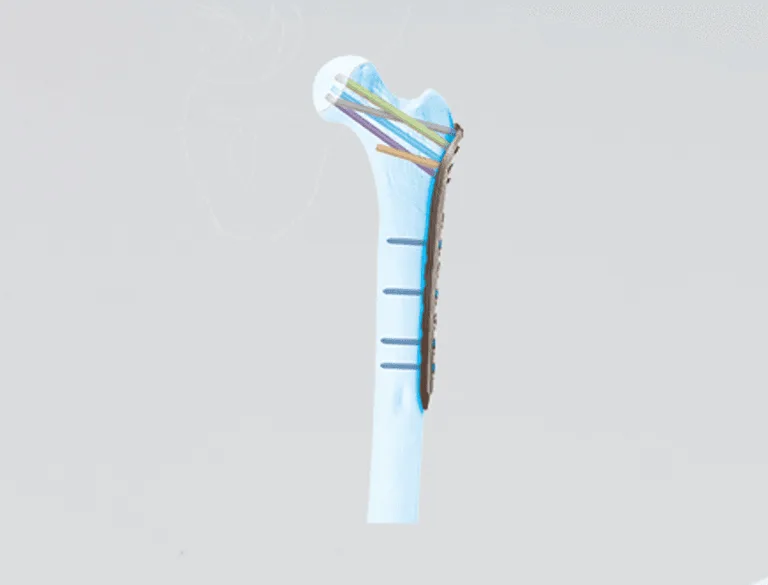
Proximal femoral locking plate is indicated for complex proximal femur fractures including subtrochanteric and pertrochanteric fractures, with pre-contoured anatomical design for angular stable fixation as an alternative or supplement to intramedullary nails.

Anterolateral distal tibial locking plate is indicated for distal tibia fractures involving anterolateral column, with pre-contoured anatomical design to provide angular stable fixation for intra- and extra-articular fractures, restoring tibial alignment and ankle joint congruity.
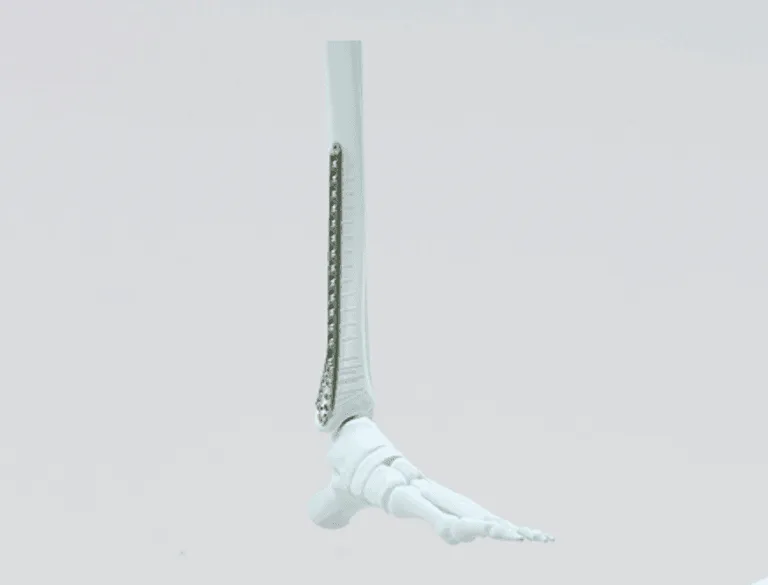
Medial distal tibial locking plate with tab is indicated for distal tibia fractures involving medial column, with extended tab design to enhance plate positioning, fixation stability and soft tissue adaptability.